📞  — free, 24/7
 — free, 24/7| Package | Price per Dose | Price | |
|---|---|---|---|
| 360 pills | £0.80 | £357.81 £286.25 Free shipping | |
| 180 pills | £0.89 | £198.78 £159.02 Free shipping | |
| 120 pills | £1.00 | £150.50 £120.40 | |
| 90 pills | £1.11 | £124.94 £99.95 | |
| 60 pills | £1.27 | £95.12 £76.10 | |
| 30 pills | £1.52 | £56.78 £45.43 | |
| 360 pills | £0.94 | £424.55 £339.64 Free shipping | |
| 180 pills | £1.06 | £237.12 £189.69 Free shipping | |
| 120 pills | £1.20 | £180.32 £144.26 | |
| 90 pills | £1.33 | £149.08 £119.26 | |
| 60 pills | £1.53 | £115.00 £92.00 | |
| 30 pills | £1.90 | £70.98 £56.79 | |
| 360 pills | £1.08 | £485.61 £388.49 Free shipping | |
| 180 pills | £1.23 | £275.46 £220.37 Free shipping | |
| 120 pills | £1.44 | £215.82 £172.65 Free shipping | |
| 90 pills | £1.59 | £178.90 £143.12 | |
| 60 pills | £1.76 | £132.04 £105.63 | |
| 30 pills | £2.01 | £75.24 £60.19 |
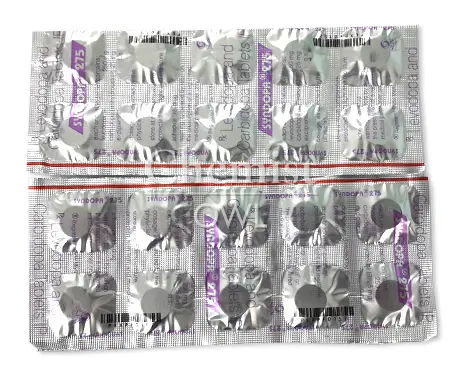
Carbidopa / Levodopa is a fixed-dose combination consisting of carbidopa, a peripheral aromatic L-amino acid decarboxylase (AADC) inhibitor, and levodopa, a dopamine precursor. The formulation increases central nervous system dopaminergic activity by delivering levodopa to the brain while reducing peripheral conversion to dopamine; it is used primarily for symptomatic treatment of Parkinson disease.
Carbidopa is a peripheral decarboxylase inhibitor that limits the peripheral conversion of levodopa to dopamine. By reducing peripheral dopamine production, it diminishes gastrointestinal and cardiovascular adverse effects and enhances the fraction of administered levodopa that reaches the brain. Levodopa acts as a prodrug; after absorption, it is transported across the blood–brain barrier and decarboxylated to active dopamine within the nigrostriatal pathway, thereby replenishing depleted central dopamine stores.
The combination thereby exploits a synergistic mechanism: carbidopa extends central availability of levodopa and permits lower peripheral dosages, while levodopa provides the substrate for central dopamine synthesis. The result is improved motor function with a lower incidence of nausea, vomiting, and orthostatic symptoms than levodopa alone. Pharmacokinetic properties are influenced by gastric motility, dietary protein, and coadministration with iron-containing products, all of which can alter absorption and peak effect timing.
Oral formulations yield rapid onset with immediate-release preparations generally producing clinical benefit within 30–60 minutes, with effects lasting several hours. Extended-release variants and combination products aim to prolong symptom control and reduce wearing-off phenomena. Regular titration guided by clinical response and tolerability is essential, as motor fluctuations may emerge with long-term therapy despite initial efficacy.
The principal indication is symptomatic management of Parkinson disease in patients with bradykinesia, rigidity, tremor, and impaired activities of daily living. Carbidopa/levodopa improves motor symptoms and can enhance gait and functional mobility, particularly in patients who exhibit a good initial response to levodopa. It remains the cornerstone of pharmacotherapy for moderate to advanced disease with fluctuating motor control.
In selected cases, carbidopa/levodopa is used as adjunctive therapy in parkinsonian syndromes characterized by dopaminergic deficiency, including some atypical parkinsonisms where levodopa responsiveness is partial. It is not disease-modifying and does not halt progression; rather, it aims to optimize symptomatic control and quality of life. Clinicians may combine it with dopaminergic agonists, MAO-B inhibitors, or COMT inhibitors to tailor duration of effect and dyskinesia risk.
Off-label or individualized use includes management of certain drug-induced extrapyramidal symptoms and dystonias where dopamine deficiency is suspected or where other agents fail to provide adequate relief. In all scenarios, treatment decisions balance motor benefit against potential adverse effects and the emergence of wearing-off or on-off fluctuations over time.
Therapy is individualized; initial regimens commonly begin with low morning doses and gradual titration to reduce nausea and hypotension while assessing motor response. A typical starting scheme uses a fixed-dose tablet containing a modest amount of levodopa with carbidopa, administered three times daily, then adjusted to achieve steady control of symptoms.
Patients are instructed to administer carbidopa/levodopa with water and to maintain a regular dosing schedule, avoiding missed doses which can precipitate return of symptoms. When adjusting dose or frequency, clinicians monitor for dyskinesias, orthostatic changes, and nocturnal symptoms, and adjust gradually over days to weeks to identify an optimal balance of efficacy and tolerability.
Formulation choice influences administration. Immediate-release tablets are taken in divided doses, typically one to three times daily, while extended-release capsules or multipart formulations are dosed less frequently but should be swallowed whole and not crushed or chewed. Administration timing in relation to meals may be adjusted to optimize absorption; small snacks may improve tolerability, whereas large protein meals can slow or reduce absorption and peak effect.
Before starting therapy, assess for contraindications such as a history of malignant melanoma or active, untreated skin lesions, since levodopa-derivative therapy may complicate melanoma detection. Exercise caution in patients with glaucoma, open-angle disease, or significant cardiac conduction abnormalities, and monitor blood pressure due to potential orthostatic hypotension. Pregnancy and lactation require careful risk-benefit assessment.
Drug interactions are clinically important. Nonselective monoamine oxidase inhibitors (MAOIs) can precipitate hypertensive crises and should be discontinued well before initiation of carbidopa/levodopa. Antipsychotic agents with strong dopamine receptor antagonism can diminish therapeutic benefit of levodopa. Iron supplements may bind levodopa in the gut, reducing absorption; separate dosing by several hours. Vitamin B6 does not affect carbidopa/levodopa efficacy, but caution with high-dose pyridoxine in the absence of decarboxylase inhibitors remains prudent.
Patients should be monitored for psychiatric and cognitive effects, including confusion, agitation, and hallucinations, especially in the elderly or when combined with other central nervous system-active medicines. Long-term therapy can lead to motor complications, including wearing-off and dyskinesias; dose adjustments or intermittent drug holidays should only be undertaken under medical supervision. If a patient experiences sudden sleep onset or severe dyskinesias, clinical assessment is warranted.
Nausea, vomiting, and loss of appetite are among the most common early adverse effects and usually respond to gradual dose titration or taking the medication with a small amount of food. Orthostatic hypotension may occur, increasing the risk of dizziness and falls, particularly in elderly individuals or during dose changes.
Dyskinesias and motor fluctuations can emerge with chronic therapy, sometimes necessitating dose adjustments, addition of a COMT or MAO-B inhibitor, or reconfiguration of the dosing schedule. Neuropsychiatric symptoms such as confusion, hallucinations, or agitation may occur, requiring clinical monitoring and, in some cases, dose modification or temporary discontinuation.
Other frequent but typically reversible effects include dry mouth, darkened urine or sweat, excessive daytime sleepiness, and sleep disturbances. Rare but serious reactions include malignant melanoma risk considerations, potential impulse control disorders, and rarer hypersensitivity or dermatologic reactions. Patients should report any new pigmented lesions or changes in mood, cognition, or behavior promptly.
14–21 days. Free from £151.46 .
5–9 days. £22.72
−10% when paying with cryptocurrency.
−10% on all repeat orders.
All orders are packed in neutral, unbranded boxes with no product name on the outside.